
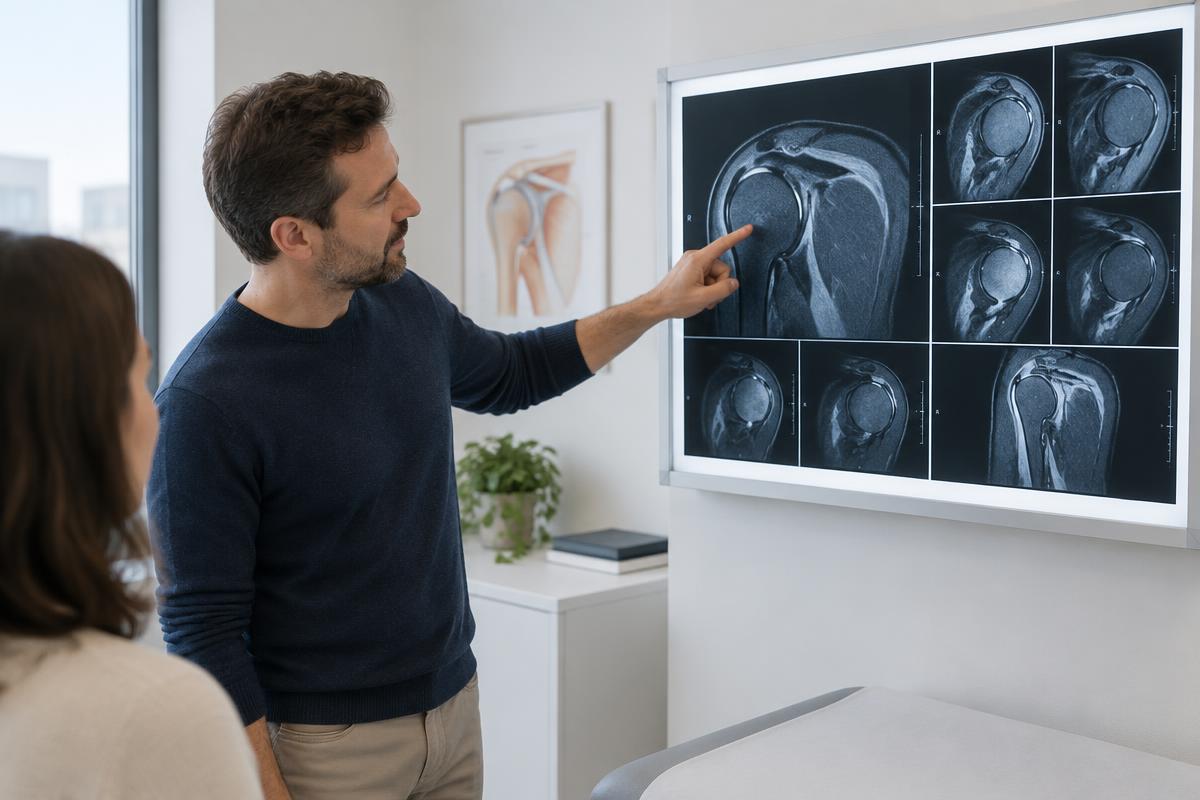

The rotator cuff is four tendons that hold the head of the humerus centered in a shallow socket while the arm moves. Supraspinatus, the tendon that runs under the bony roof of the shoulder, does the most work and fails the most often. Years of overhead work, load carriage, and repetitive lifting wear it thin; a single fall or catch can tear it outright.
Rotator cuff claims are common and frequently denied, usually for one specific reason covered below.
How the VA rates it
There is no diagnostic code that says rotator cuff. The condition is rated on what it does to the joint, which in nearly every case means limitation of arm motion under DC 5201: 20 percent at shoulder level, 30 percent major or 20 percent minor at midway, and 40 percent major or 30 percent minor at 25 degrees from the side.
Where motion is preserved but painful, 38 CFR 4.59 supports the minimum compensable 10 percent for the joint. Tendinitis and bursitis are rated by analogy under codes that themselves direct rating on limitation of motion. Our shoulder rating guide lays out each percentage in full.
Why these claims get denied
The usual denial reads some version of this: the imaging shows degenerative changes consistent with age, and there is no evidence of an in-service shoulder injury. Rotator cuff pathology genuinely is common in the general population as people age, and the VA leans on that.
What answers it is not an argument that aging plays no role. It is a medical explanation of why this veteran's cuff failed the way it did, when it did. That means addressing cumulative load, documented duty demands, the pattern and location of the tear, and the veteran's history relative to what would be expected without that service history. A credible opinion engages with the degenerative explanation rather than ignoring it.
Our guide to why VA claims get denied covers how to identify which element the decision actually turned on.
Evidence that carries weight
For a rotator cuff claim, the strongest files usually contain:
- Imaging - MRI or ultrasound identifying the specific tendon, whether the tear is partial or full thickness, and any retraction or muscle atrophy
- A clinical examination documenting positive impingement or cuff testing and measured range of motion
- Service evidence of the physical demands - duty descriptions, job assignments, and any documented injury, no matter how brief the entry
- Lay statements from people who saw you favoring the arm, sleeping poorly on that side, or avoiding overhead work
- A continuous treatment history after separation, or a credible explanation of any long gap
Our shoulder evidence guide organizes the whole file by claim element, and our records guide shows what to gather.
Where veterans start
Every case is different, and there is no obligation at any step. When veterans want to understand what their records actually support, these are the two most common starting points:
- Medical records review
A licensed physician reviews your records for a $250 flat fee and identifies which conditions the available evidence may support. The fee is refunded in full if nothing supportable is identified.
- Nexus letter
When the records support one, a licensed provider writes the medical opinion that addresses the link between your condition and your service or an already service-connected disability.
After surgery
A repaired cuff is still a disability if function remains limited. The rating is based on the condition as it exists now, including residual weakness, restricted motion, and pain. Surgical scars that are painful or unstable can be rated separately, and a period of convalescence following surgery may support a temporary total evaluation.
Veterans sometimes assume a successful repair ends the claim. What matters is measured function and documented symptoms after recovery, not the operative report alone.
Related conditions
Chronic cuff problems rarely stay isolated. Compensating with the other arm, altered posture, and sleep disruption from night pain are all patterns the VA sees, and 38 CFR 3.310 allows secondary service connection when the medical evidence supports the link. Our shoulder secondary conditions guide covers those claims, and if numbness or weakness travels down the arm, read the brachial neuritis guide.
Impingement syndrome
Impingement syndrome develops when the space under the acromion narrows and the rotator cuff tendons and the bursa above them get pinched with overhead motion. It is one of the most frequently diagnosed shoulder conditions in veterans who spent years reaching overhead, whether that meant maintenance work, loading equipment, or repetitive lifting above shoulder height.
Impingement is not a separate diagnostic code either. It is rated the same way as a rotator cuff tear: on the limitation of arm motion it produces under DC 5201, or at the minimum compensable rating under 38 CFR 4.59 where motion is preserved but painful. Clinically, impingement is often the earlier stage of the same process that later produces a partial or full thickness tear, so the medical evidence in the file should describe the full progression rather than treating each finding as an isolated event.
A positive Neer or Hawkins impingement sign on examination, documented in the treatment record or on the Shoulder and Arm Conditions Disability Benefits Questionnaire, supports the diagnosis. Because impingement can also result from bony anatomy present before service, an opinion addressing that alternative explanation strengthens the file the same way it does for a degenerative tear.
Adhesive capsulitis and stiffness
Some veterans develop adhesive capsulitis, commonly called frozen shoulder, either on its own or following a cuff injury or surgery. The capsule thickens and motion becomes restricted in every direction, not only overhead, which distinguishes it clinically from a simple cuff tear.
Because the limitation affects flexion, abduction, and rotation together, the rating is still measured under DC 5201 using whichever measurement, flexion or abduction, shows the greater restriction. Documentation should include measurements in multiple planes, since a frozen shoulder that is missed in a single-plane exam can understate the actual functional loss.
Frozen shoulder frequently follows a period of guarding after an injury or surgery, so a treatment record showing that sequence helps connect the stiffness back to the original service-connected event rather than leaving it looking like an unrelated new condition.
When rotator cuff and instability overlap
A significant rotator cuff tear can allow the head of the humerus to migrate within the joint, and chronic instability can in turn wear down the cuff tendons that are supposed to stabilize it. When both problems exist together, the file should describe which came first and how they relate, because the VA rates the joint once under whichever code, DC 5201 or DC 5202, better captures the actual impairment, rather than under both for the same limitation.
Our shoulder instability guide explains the dislocation criteria in detail for veterans whose cuff problems developed alongside a shoulder that comes out of place.
Frequently asked questions
What VA rating do I get for a torn rotator cuff?
There is no diagnostic code specific to the rotator cuff. Once service connected, the condition is almost always rated under Diagnostic Code 5201 for limitation of arm motion in 38 CFR 4.71a, at 20, 30, or 40 percent depending on how far the arm can be raised and whether the affected arm is dominant under 38 CFR 4.69.
Can I get a VA rating for a rotator cuff tear that has not been repaired?
Yes. Surgery is not required for service connection or a rating. What matters is a current diagnosis supported by imaging or a clinical examination, and documented functional loss such as limited motion, pain, or weakness. An untreated tear can still be rated on the same limitation of motion criteria as a repaired one.
Why did the VA deny my rotator cuff claim as degenerative?
This is the most common denial reason. The VA often points to imaging findings described as degenerative and concludes the condition is age-related rather than service-connected. A medical opinion that specifically addresses cumulative service loading, the documented duty demands, and why this veteran's cuff failed when it did can respond to that reasoning.
Is a partial thickness tear rated differently than a full thickness tear?
The rating schedule does not assign a different percentage based on tear thickness. Both are rated on the resulting limitation of arm motion or, where motion is preserved but painful, at the minimum compensable rating under 38 CFR 4.59. The imaging finding matters for diagnosis and for the medical opinion, not for a separate rating tier.
Sources
- 38 CFR 4.71a - Schedule of ratings, musculoskeletal system (eCFR)
- 38 CFR 4.59 - Painful motion (eCFR)
- 38 CFR 4.40 - Functional loss (eCFR)
- 38 CFR 3.303 - Principles relating to service connection (eCFR)
- 38 CFR 3.310 - Secondary service connection (eCFR)
- VA Form 21-0960M-12, Shoulder and Arm Conditions Disability Benefits Questionnaire