
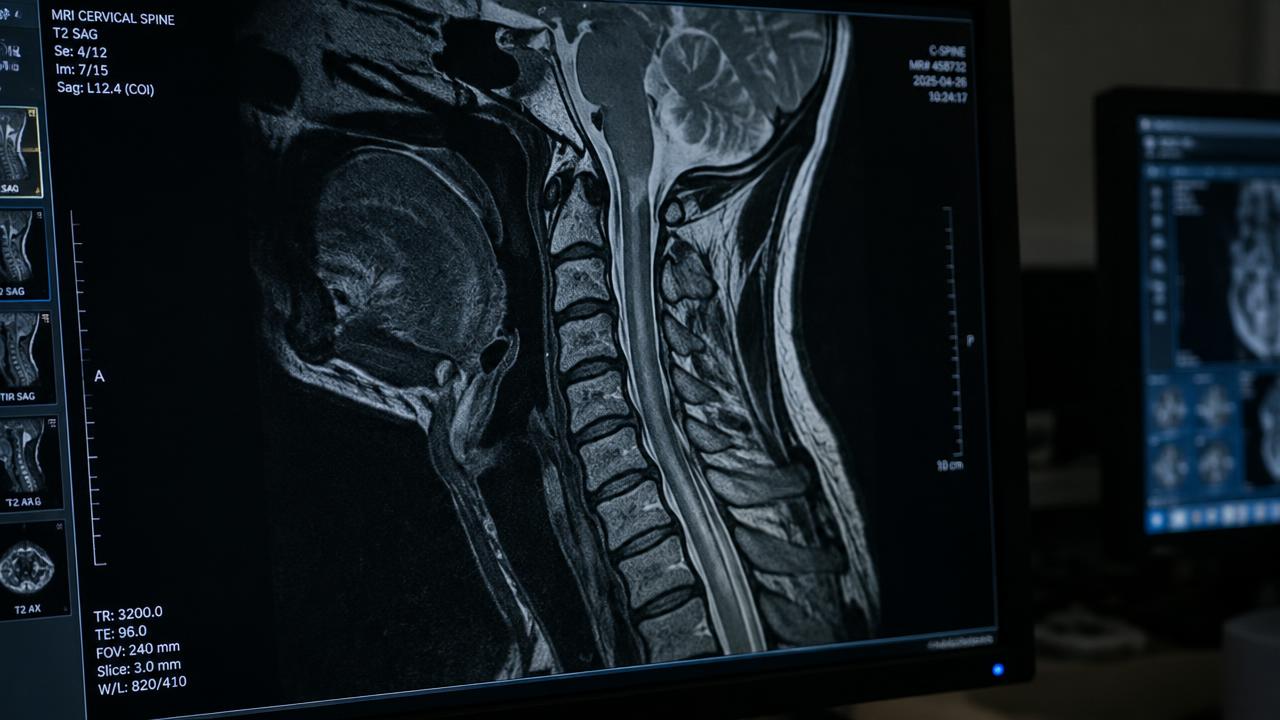

Cervical degenerative disc disease is a wear pattern: discs lose height and hydration, the spaces between vertebrae narrow, bone spurs form, and the joints that guide motion become arthritic. On an MRI report it reads as disc desiccation, disc space narrowing, osteophyte formation, or foraminal narrowing.
The clinical picture is stiffness that is worst in the morning, grinding with rotation, pain that spreads into the shoulder blade, and sometimes numbness in an arm when a narrowed opening irritates a nerve root.
Why imaging alone does not win the claim
Degenerative change is extremely common with age, and VA examiners regularly attribute it to the normal aging process. That is the single most common reason these claims are denied.
A useful opinion does not argue that aging plays no role. It explains why the pattern in this veteran - the level involved, the asymmetry, the age at onset, the documented loading in service, the continuity of symptoms since - is more consistent with accelerated degeneration from service than with ordinary aging alone. Our guide to why VA claims get denied covers how that reasoning gap shows up in decision letters.
The service evidence that matters
Neck degeneration claims usually rest on cumulative loading rather than a single accident. The record is stronger when it captures the specific demands the neck absorbed.
- Duty assignments involving helmets with mounted optics and counterweights, body armor, or heavy load carriage
- Airborne operations, vehicle rollovers, hard landings, or blast exposure
- Any documented neck or upper back complaint, even a single sick call visit
- Post-service treatment history showing continuity from separation forward
- Lay statements describing limits others personally observed
How it is rated
Regardless of the diagnostic label, evaluation runs through the General Rating Formula, explained in our cervical spine rating guide. Where disc disease produces physician-prescribed bed rest, the incapacitating episodes method described in our IVDS guide may produce a higher evaluation.
If nerve root irritation causes numbness, weakness, or reflex changes in an arm, that is rated separately - see our cervical radiculopathy guide.
Where veterans start
Every case is different, and there is no obligation at any step. When veterans want to understand what their records actually support, these are the two most common starting points:
- Medical records review
A licensed physician reviews your records for a $250 flat fee and identifies which conditions the available evidence may support. The fee is refunded in full if nothing supportable is identified.
- Nexus letter
When the records support one, a licensed provider writes the medical opinion that addresses the link between your condition and your service or an already service-connected disability.
Degeneration secondary to another condition
Under 38 CFR 3.310, cervical degeneration can also be secondary. A service-connected shoulder injury that changed how you carry load, or a service-connected lumbar condition that altered posture and gait, can accelerate wear in the neck. Aggravation counts as well: a pre-existing condition made permanently worse by a service-connected disability is compensated for the degree of worsening.
Our neck secondary conditions guide works through those pathways in both directions.
Cervical facet arthropathy and the difference from disc disease
Degenerative disc disease refers to the discs themselves losing height and hydration. A related but distinct finding, facet arthropathy, is arthritis in the small paired joints at the back of each vertebra that guide rotation and side bending. The two frequently appear together on the same imaging report because they share a common mechanical cause: as a disc narrows, more load transfers onto the facet joints behind it, accelerating wear there as well.
For rating purposes the distinction rarely matters, because both are evaluated under the same General Rating Formula in 38 CFR 4.71a based on measured motion rather than the specific structure involved. It matters more for the medical opinion, since an examiner who sees facet arthropathy without disc space narrowing may be more inclined to attribute it to age. A well-supported opinion addresses whichever finding is actually present in the imaging rather than treating the two terms as interchangeable.
Multilevel disease and which level to claim
Cervical MRI reports frequently show degeneration at more than one level, most often C5-C6 and C6-C7 since these segments carry the most motion and load. The VA does not require a claim to isolate a single level. The cervical spine is rated as a whole under the General Rating Formula, so the percentage reflects the combined effect on motion regardless of how many levels are involved.
Level-specific detail still matters for the neurologic side of the claim. A nerve root compressed at C6 produces a different pattern of numbness and weakness than one compressed at C7, and an examiner's opinion on radiculopathy is more persuasive when it matches the anatomic level shown on imaging to the specific symptoms described.
Surgical history and post-surgical residuals
Some veterans with advanced cervical degenerative disc disease eventually undergo a cervical fusion or disc replacement. Surgery does not end the claim; it usually changes what is being rated. A fused segment often results in ankylosis of that portion of the spine, which is evaluated under the same General Rating Formula using the ankylosis criteria rather than a range-of-motion measurement, since a fused joint cannot move.
Scarring from the surgical approach, whether anterior or posterior, can also support a separate rating under the scar criteria in 38 CFR 4.118 where the scar is painful or unstable. Any hardware complications, continued radiculopathy despite surgery, or adjacent segment degeneration that develops at levels next to the fusion are evaluated on their own merits using current findings after the surgery.
Frequently asked questions
What VA rating is degenerative disc disease of the neck?
Cervical degenerative disc disease is rated under the General Rating Formula in 38 CFR 4.71a, at 10, 20, 30, or 40 percent based on measured motion, spasm or guarding, and ankylosis. If the condition involves intervertebral disc syndrome, it can instead be rated on incapacitating episodes, whichever method gives the higher evaluation.
Does an MRI showing degeneration prove service connection?
No. Imaging establishes a current diagnosis, which is only the first element. The claim still needs an in-service event or a service-connected primary condition, plus a medical opinion connecting the two. Degenerative changes are common in the general population, so the opinion has to explain why service accounts for this veteran's pattern.
Is degenerative arthritis of the neck presumptive?
Arthritis is a chronic disease under 38 CFR 3.309(a), so it may be presumed service connected if it became manifest to a compensable degree within one year of separation. Outside that year, the ordinary direct or secondary rules apply.