
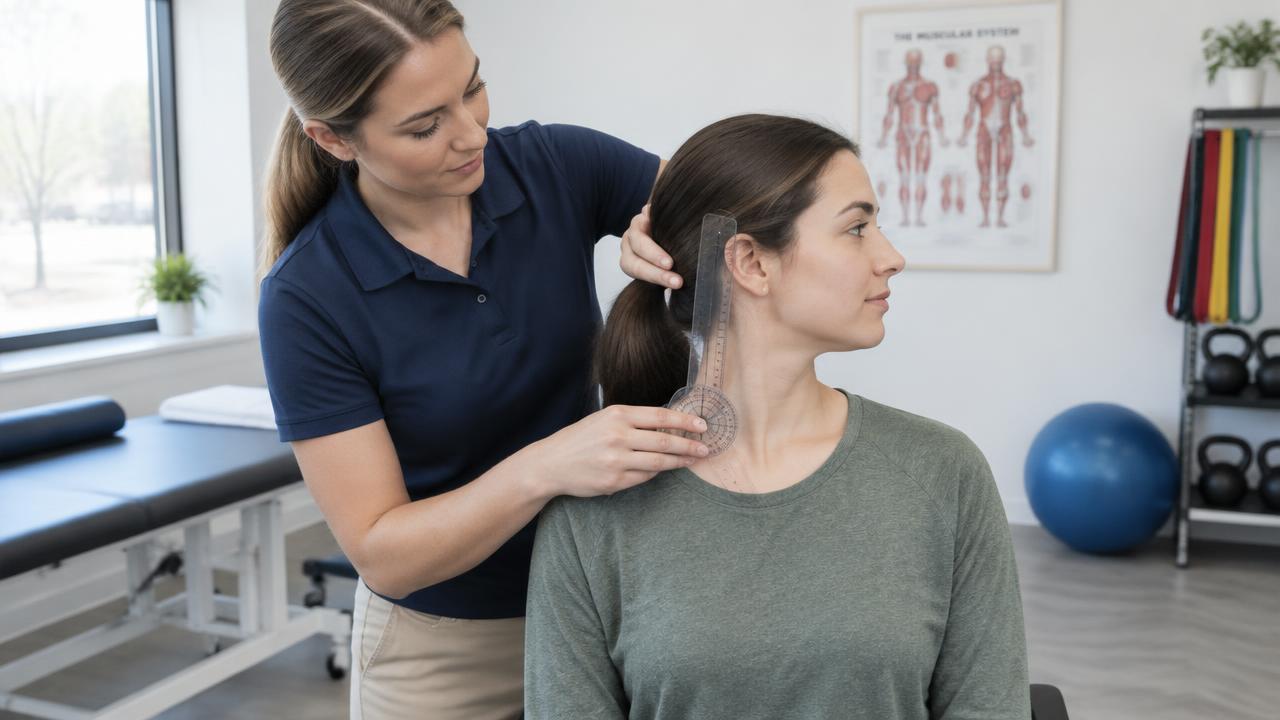

Neck ratings are mechanical. The VA measures how far the neck moves, notes whether spasm or guarding is present, and reads the result off a table. Understanding the table explains why two veterans with similar pain can end up at very different percentages.
Cervical spine conditions are evaluated under the General Rating Formula for Diseases and Injuries of the Spine in 38 CFR 4.71a. The formula applies regardless of the underlying diagnosis - strain, arthritis, degenerative disc disease, or stenosis are all measured the same way.
The cervical spine criteria
The percentages below apply when the condition affects the cervical spine. The thoracolumbar spine has its own set of numbers in the same formula.
- 10 percent - forward flexion greater than 30 degrees but not greater than 40 degrees; or combined range of motion greater than 170 degrees but not greater than 335 degrees; or muscle spasm, guarding, or localized tenderness not resulting in abnormal gait or abnormal spinal contour; or a vertebral body fracture with loss of 50 percent or more of height
- 20 percent - forward flexion greater than 15 degrees but not greater than 30 degrees; or combined range of motion not greater than 170 degrees; or muscle spasm or guarding severe enough to result in abnormal gait or abnormal spinal contour such as scoliosis, reversed lordosis, or abnormal kyphosis
- 30 percent - forward flexion of the cervical spine 15 degrees or less; or favorable ankylosis of the entire cervical spine
- 40 percent - unfavorable ankylosis of the entire cervical spine
- 100 percent - unfavorable ankylosis of the entire spine
How combined range of motion is figured
Combined range of motion is the sum of six measurements: forward flexion, extension, left and right lateral flexion, and left and right rotation. Normal values are 45 degrees of flexion, 45 of extension, 45 of lateral flexion each side, and 80 of rotation each side - a normal combined total of 340 degrees.
Each measurement is rounded to the nearest five degrees, and any measurement above the normal maximum is counted at the normal value. That is why a veteran can have painfully limited rotation and still land at 10 percent if flexion remains fairly good.
Painful motion and functional loss
The numbers on the exam sheet are not the whole story. Under 38 CFR 4.59, painful motion is entitled to at least the minimum compensable rating for the joint, and the point at which pain begins is the measurement that counts - not how far the joint can be pushed.
38 CFR 4.40 and 4.45 require the examiner to account for functional loss: weakness, fatigability, incoordination, and loss of endurance, including after repetitive use and during flare-ups. A neck that moves reasonably well in a quiet exam room but locks up after two hours of driving is supposed to be rated on the worse picture, which only happens if the record documents it.
Our C&P exam guide for neck claims covers how to describe those limits accurately at the exam.
What gets rated separately
Note 1 to the General Rating Formula directs the VA to evaluate any associated objective neurologic abnormalities separately under an appropriate diagnostic code. For the neck, that usually means radiculopathy in an arm, rated under 38 CFR 4.124a and covered in our cervical radiculopathy guide.
Intervertebral disc syndrome may be rated either under this formula or on incapacitating episodes, whichever produces the higher evaluation - see our IVDS guide.
Separate ratings do not add together. They combine under the table in 38 CFR 4.25, which our combined rating calculator applies.
Where veterans start
Every case is different, and there is no obligation at any step. When veterans want to understand what their records actually support, these are the two most common starting points:
- Medical records review
A licensed physician reviews your records for a $250 flat fee and identifies which conditions the available evidence may support. The fee is refunded in full if nothing supportable is identified.
- Nexus letter
When the records support one, a licensed provider writes the medical opinion that addresses the link between your condition and your service or an already service-connected disability.
Ratings, evidence, and increases
A rating increase is a severity question, not a causation question. If the neck is service connected already and the percentage no longer matches the limitation, the evidence that moves it is current measurement and documented functional loss - not another opinion about how it started. Our guide to nexus letters and increased ratings explains that distinction.
Bilateral factors and combined orthopedic ratings
The cervical spine is a single, midline structure, so the bilateral factor that applies to paired limbs does not come into play for the neck rating itself. It becomes relevant only when a separate neurologic rating affects both arms, since 38 CFR 4.26 adds a small bilateral factor when disabilities affect corresponding paired extremities.
Veterans sometimes assume a neck rating and a shoulder rating on the same side will be reduced against each other because they involve overlapping muscles. They are not. Each diagnostic code is evaluated on its own criteria, and the results are combined under the table in 38 CFR 4.25 rather than adjusted for anatomic overlap, unless a specific pyramiding rule in 38 CFR 4.14 prohibits compensating the same manifestation twice under two different codes.
Avoiding pyramiding
38 CFR 4.14 prohibits evaluating the same disability, or the same manifestation of a disability, under two different diagnostic codes. For the cervical spine this comes up most often with muscle spasm: spasm that is already accounted for in the General Rating Formula percentage cannot also be rated separately as a muscle disability under 38 CFR 4.73.
It does not prevent separate ratings for genuinely distinct impairments. Loss of cervical motion, radiculopathy in an arm, and a cervicogenic headache disorder are three different manifestations arising from one underlying condition, and 38 CFR 4.71a's Note 1 specifically directs that the neurologic component be rated separately. The line is whether the two ratings would compensate the identical symptom twice or two different symptoms once each.
How a rating can change over time
Spine ratings are not fixed for life. If range of motion worsens, an increased rating claim documents the new measurements the same way the original claim did, through updated range-of-motion testing and a description of functional loss on an average day.
The reverse is also possible. Under 38 CFR 3.344, a rating that has been in effect for five years or more is protected from reduction unless sustained improvement is shown by full examinations and the improvement reflects actual functioning under the ordinary conditions of life, not just a single good exam. Ratings in place for less than five years receive less procedural protection but still require the VA to follow due process before reducing them, including a proposed reduction and an opportunity to respond.
- A rating increase requires new measurements showing a worse cervical range of motion or new ankylosis
- A proposed reduction must be based on material improvement shown by the whole record, not an isolated exam
- Ratings of 20 years or more become permanent and protected from reduction except in cases of fraud, under 38 CFR 3.951
Frequently asked questions
What is the highest VA rating for a neck condition?
Under the General Rating Formula, the cervical spine alone tops out at 40 percent, which requires unfavorable ankylosis of the entire cervical spine. A 100 percent evaluation requires unfavorable ankylosis of the entire spine. Separate ratings for nerve involvement can raise the combined total above the spine rating itself.
What range of motion gets 20 percent for the neck?
Forward flexion of the cervical spine greater than 15 degrees but not greater than 30 degrees, or a combined range of motion not greater than 170 degrees, or muscle spasm or guarding severe enough to result in an abnormal gait or abnormal spinal contour.
What is normal cervical range of motion?
Normal cervical forward flexion and extension are each 0 to 45 degrees, lateral flexion is 0 to 45 degrees in each direction, and rotation is 0 to 80 degrees in each direction, for a normal combined range of 340 degrees.
Does pain during motion affect the rating?
Yes. Under 38 CFR 4.59 the point at which pain begins during motion is the measurement that matters, and 38 CFR 4.40 requires functional loss from pain, weakness, fatigability, and lack of endurance to be considered, including after repeated use and during flare-ups.