
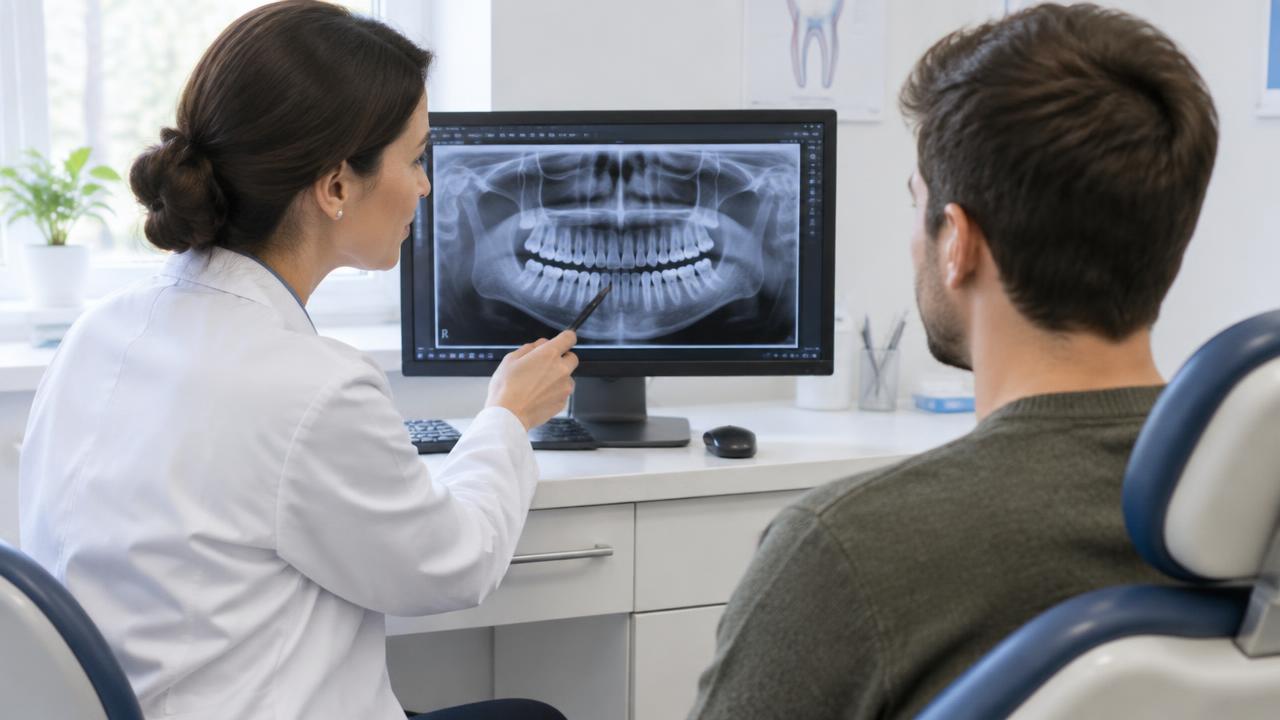

Losing teeth changes what a person can eat, how they speak, and how they feel in a room. The VA does compensate for it, but under narrower terms than most veterans expect, and the cause of the loss matters more than the number of teeth.
What Diagnostic Code 9913 actually rates
Diagnostic Code 9913 in 38 CFR 4.150 covers loss of teeth due to loss of substance of the body of the maxilla or mandible without loss of continuity. Ratings run from 0 percent where the lost masticatory surface can be restored by a suitable prosthesis, up to 40 percent where all teeth are lost and no prosthesis can restore the surface.
The percentage depends on two things: how much of the arch is affected, and whether a prosthesis can restore function. A veteran with a well-fitting denture will usually sit at 0 percent even with extensive loss, which surprises people until they read the code.
The cause requirement
The note under the code limits it to loss resulting from trauma or from disease such as osteomyelitis, and excludes loss due to periodontal disease. This is why the same extraction can be compensable for one veteran and not another. Our periodontal disease guide explains the treatment-only rule that applies to the excluded causes.
In-service trauma is the cleanest path. A documented facial injury, a vehicle accident, an assault, or a training injury that fractured the jaw or knocked out teeth creates a direct line. Those cases often also involve fracture residuals rated under codes 9902 through 9904 - see our jaw fracture guide.
Medication-related decay and dry mouth
The path that gets overlooked is secondary. Under 38 CFR 3.310, a disability caused or aggravated by a service-connected condition is service connected. Reduced salivary flow is a well-documented side effect of many medications prescribed for service-connected conditions, including selective serotonin reuptake inhibitors and other antidepressants, anxiolytics, several antihypertensives, muscle relaxants, and opioid pain medications.
Saliva protects teeth. When it drops, decay accelerates, existing restorations fail, and teeth are eventually lost. A medical opinion that ties the prescription record to the documented xerostomia and then to the dental deterioration is doing real work, and it is exactly the kind of reasoning our nexus letter explainer describes.
Where the same picture involves mental health treatment, our mental health series covers the primary conditions those prescriptions usually treat.
Aggravation counts too
Secondary service connection is not limited to conditions a service-connected disability caused outright. Aggravation of a pre-existing dental condition is also covered, which matters for veterans who had some decay before the medications started. The opinion should describe the baseline and the worsening separately.
Where veterans start
Every case is different, and there is no obligation at any step. When veterans want to understand what their records actually support, these are the two most common starting points:
- Medical records review
A licensed physician reviews your records for a $250 flat fee and identifies which conditions the available evidence may support. The fee is refunded in full if nothing supportable is identified.
- Nexus letter
When the records support one, a licensed provider writes the medical opinion that addresses the link between your condition and your service or an already service-connected disability.
Building the file
Pull the complete pharmacy record with start dates, the full dental chart including every extraction and its stated reason, imaging that shows bone levels and the pattern of decay, and any note where a dentist or physician recorded dry mouth. Statements describing the practical effect - what you cannot chew, the weight change, the switch to softer foods - support the functional picture. The general structure is in our evidence checklist.
Dietary restriction also matters if a jaw joint condition is in play, because the higher tiers of Diagnostic Code 9900 combine limited opening with diet.
How much of the arch has to be affected
Diagnostic Code 9913 scales with how much of the dental arch is involved, not just whether teeth are missing. A veteran missing a few teeth in a limited area, where a partial denture restores function, sits at the lower end of the scale or at 0 percent. A veteran who has lost most or all teeth in both arches, particularly where bone loss prevents a full denture from fitting or functioning properly, is evaluated toward the higher end of the code.
This is why the prosthodontic evaluation matters as much as the extraction history. A dental record noting that a denture does not fit properly because of insufficient supporting bone, rather than simply noting that teeth are missing, is the kind of finding that supports a higher percentage.
Interaction with TMJ and dietary restriction claims
Tooth loss and jaw joint disorders often appear in the same veteran's file, and the two can be considered together without violating pyramiding rules as long as each rated disability reflects a distinct impairment. Significant tooth loss that also limits what a veteran can chew may support the dietary restriction element used in the higher tiers of Diagnostic Code 9900, in addition to whatever rating applies under Diagnostic Code 9913 for the tooth loss itself.
Veterans building a claim around both conditions should make sure the dietary and functional limitations are described specifically at any exam, since these details can affect more than one part of the claim.
Where veterans go from here
If the loss traces to trauma in service, the direct claim is usually straightforward. If it traces to medications, the claim needs a medical opinion that walks the chain. A records review identifies which of those the documentation supports before anything is written.
Frequently asked questions
Does the VA compensate for every lost tooth?
No. Diagnostic Code 9913 only rates tooth loss due to loss of substance of the maxilla or mandible caused by trauma or disease such as osteomyelitis. Ordinary tooth loss from decay or periodontal disease is generally not compensable, though it may support VA dental treatment eligibility under separate rules.
Does wearing dentures affect my tooth loss rating?
Yes. Diagnostic Code 9913 rates lower where a suitable prosthesis, such as a well-fitting denture, can restore the lost masticatory surface. A veteran with extensive tooth loss but a functional denture may be rated 0 percent, while a veteran whose bone loss prevents a prosthesis from working can be rated higher.
Can medications for PTSD or depression cause a compensable dental claim?
Reduced saliva flow from medications prescribed for a service-connected condition can accelerate decay and tooth loss, which may support a secondary service connection claim under 38 CFR 3.310 when a medical opinion documents the medication, the dry mouth, and the resulting dental damage.
What if my teeth were healthy before service but decayed afterward without a specific injury?
Without a qualifying cause such as trauma, disease like osteomyelitis, or a documented secondary pathway such as medication-related dry mouth, gradual decay after service is generally treated as ordinary dental disease and is not compensable under Diagnostic Code 9913.